

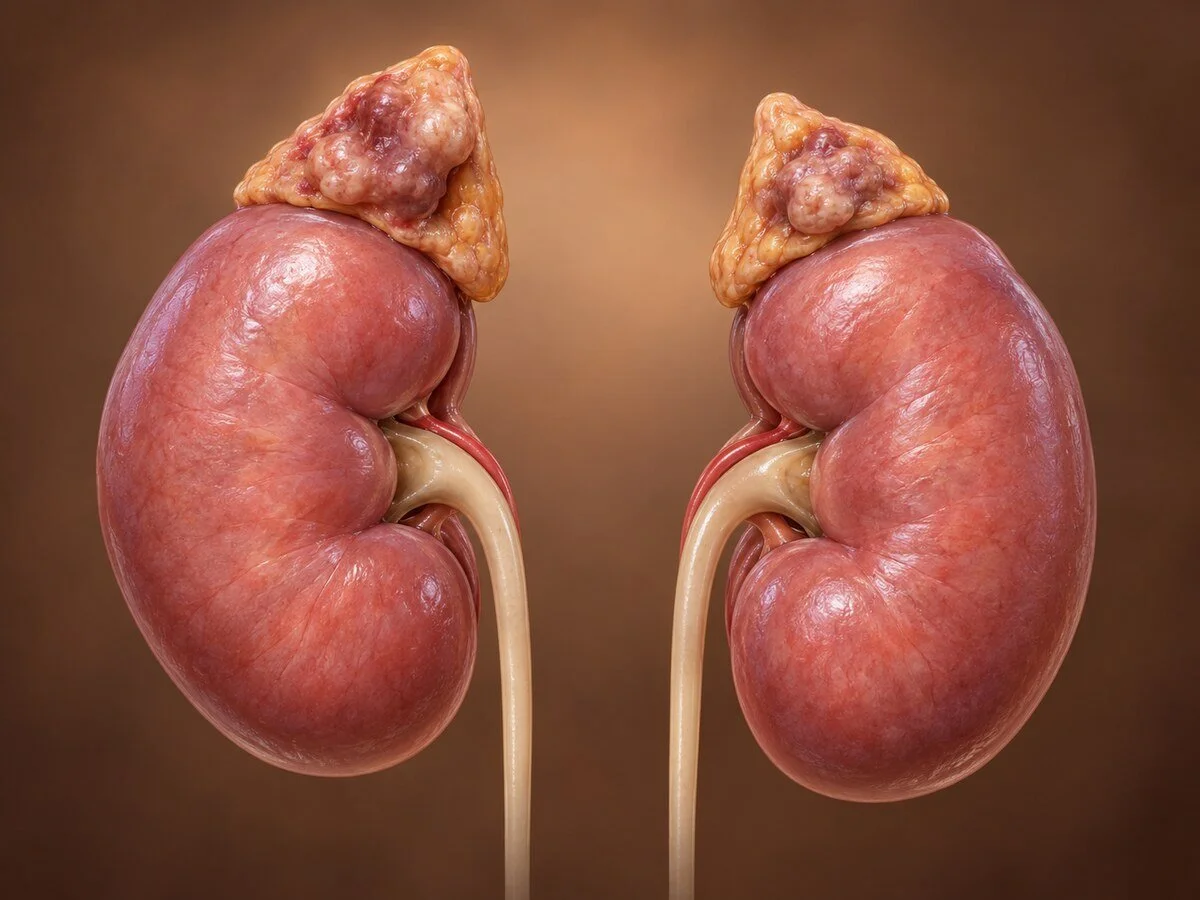
The adrenal glands are one of the commonest sites for cancer to spread. In a patient with a known cancer, an adrenal mass is a metastasis until proved otherwise — a complete reversal of the probabilities that apply to an adrenal mass found in someone with no cancer history, where the overwhelming likelihood is a harmless adenoma. Getting that distinction right matters because it determines whether the patient is treated for localised disease with curative intent or for metastatic disease, and the difference in treatment is total.
The second point worth making early is a hopeful one: an isolated adrenal metastasis is not necessarily the end of curative treatment. In selected patients — particularly with lung cancer, renal cell carcinoma and melanoma — removing a solitary adrenal deposit produces long-term survival in a meaningful proportion.
How they form
The adrenal glands receive a disproportionately rich blood supply for their size — among the highest per gram of tissue in the body — drawn from three sources: the superior suprarenal arteries from the inferior phrenic, the middle suprarenal directly from the aorta, and the inferior suprarenal from the renal artery. These vessels break up into a dense subcapsular plexus of sinusoids before draining into a single central vein.
That vascular architecture is the explanation for the gland's vulnerability. Tumour cells arriving in this slow-flowing, high-volume sinusoidal bed lodge readily, and the cortex provides a lipid-rich, steroid-rich microenvironment that appears to favour their survival. Metastases typically begin in the subcapsular region and grow inward.
The commonest primary sites, in approximate order:
Lung — both non-small cell and small cell; by far the commonest source
Breast
Renal cell carcinoma — which may spread to the opposite adrenal by haematogenous routes, or to the ipsilateral gland by direct extension or lymphatic spread
Melanoma
Gastrointestinal cancers — colorectal, gastric, oesophageal, pancreatic
Lymphoma — which may involve the adrenals, often bilaterally
hepatocellular carcinoma, thyroid, prostate, ovary
Bilateral involvement is common, and this raises a specific clinical concern discussed below.
Symptoms
Most adrenal metastases cause nothing and are found on staging or surveillance imaging.
flank or back pain when large
haemorrhage into a metastasis, causing sudden pain
symptoms of the primary tumour or of disease elsewhere
Adrenal insufficiency — uncommon but important. It requires destruction of more than ninety per cent of both glands, so it occurs only with extensive bilateral involvement. The features are non-specific and easily attributed to the cancer or its treatment: fatigue, anorexia, weight loss, nausea, dizziness on standing, hypotension, low sodium, raised potassium, and hyperpigmentation. It is frequently missed, and it is fatal if unrecognised. Any patient with bilateral adrenal metastases who becomes unexpectedly unwell, hypotensive or hyponatraemic should be assessed for adrenal insufficiency and treated empirically with hydrocortisone while awaiting results.
Metastases do not produce hormones — they are not functioning tumours — so features of cortisol, aldosterone or catecholamine excess point away from metastasis and toward a primary adrenal lesion.
How the diagnosis is made
The task is distinguishing a metastasis from the very common benign adenoma, which may coexist with cancer by coincidence — and in patients with a known malignancy, a significant proportion of adrenal masses still turn out to be benign adenomas.
Unenhanced CT with Hounsfield unit measurement — the single most useful test. An attenuation of 10 HU or less indicates a lipid-rich benign adenoma and effectively excludes metastasis. Metastases are lipid-poor and denser.
Contrast washout CT — adenomas wash out contrast rapidly; metastases retain it. Absolute washout above 60% and relative washout above 40% indicate an adenoma.
Chemical shift MRI — demonstrating intracellular lipid by signal drop on opposed-phase imaging, again indicating adenoma.
FDG PET-CT — particularly valuable in the oncological setting. Uptake above that of the liver suggests metastasis. False positives occur with inflammatory lesions and occasionally adenomas; false negatives with small or mucinous lesions.
Interval growth — a lesion that enlarges on serial imaging in a patient with cancer is a metastasis until proved otherwise.
Biopsy — this is the one clear indication for adrenal biopsy. It is appropriate where imaging is indeterminate and the result would change management, and only after phaeochromocytoma has been excluded biochemically with plasma or urinary metanephrines. That step is not optional, and skipping it has caused deaths.
Assessment of adrenal function — a short Synacthen test where both glands are involved or the patient is unexpectedly unwell.
Treatment
Treatment depends entirely on whether the adrenal deposit is the only site of disease.
Isolated adrenal metastasis — treatment with curative intent
Where the primary tumour is controlled and the adrenal is the only site of spread, local treatment is worthwhile and can achieve long survival. The factors favouring it are:
a long disease-free interval between the primary and the metastasis — the strongest predictor
a controlled or resected primary
no other sites of disease on thorough staging, including PET-CT
favourable tumour biology — renal cell carcinoma, melanoma and non-small cell lung cancer are the tumours in which this approach is best established
adequate fitness
Options:
Laparoscopic adrenalectomy — appropriate for most isolated metastases, with low morbidity and short recovery. Open surgery is preferred where there is local invasion or the lesion is very large.
Stereotactic body radiotherapy — highly effective for local control, non-invasive, and a good option for patients unfit for or unwilling to undergo surgery.
Thermal ablation — radiofrequency or microwave, for small lesions; care is needed as ablation can provoke a hypertensive response.
Widespread metastatic disease
The adrenal deposit is treated as part of the systemic disease — with chemotherapy, targeted therapy or immunotherapy according to the primary tumour and its molecular profile. Local treatment may still be offered for pain or for a lesion causing local problems.
Adrenal insufficiency
Where both glands are extensively involved, or after bilateral adrenalectomy, lifelong glucocorticoid and mineralocorticoid replacement is required. Patients need clear education about sick-day dosing, a steroid card, an emergency hydrocortisone injection and training in its use. This is genuinely life-saving and is too often handled as an afterthought in a patient whose attention is on the cancer.
A specific and increasingly relevant cause of adrenal insufficiency in oncology patients is immune checkpoint inhibitor therapy, which can cause hypophysitis with secondary adrenal insufficiency, or rarely primary adrenalitis. The presentation overlaps exactly with cancer-related fatigue, and it requires a deliberately low threshold for testing.
Recovery
After laparoscopic adrenalectomy for an isolated metastasis, hospital stay is typically one to two nights with return to normal activity in two to four weeks. Where only one gland is removed and the other is normal, no hormone replacement is needed. Stereotactic radiotherapy is delivered over a small number of outpatient sessions with minimal recovery.
Follow-up
Determined by the primary cancer's surveillance protocol, with attention to the contralateral adrenal. Patients on replacement therapy require endocrine follow-up alongside their oncological care.
When to seek an opinion
An adrenal mass in a patient with cancer should be characterised properly rather than assumed to be a metastasis — a wrongly assumed metastasis can deny a patient curative treatment of their primary tumour. Conversely, an isolated adrenal metastasis should prompt discussion of local treatment rather than an automatic move to palliative systemic therapy. Unexplained fatigue, dizziness, low blood pressure or low sodium in a patient with bilateral adrenal deposits or on immunotherapy requires urgent assessment for adrenal insufficiency.
Common questions
A spot has been found on my adrenal gland. Does that mean my cancer has spread?
Not necessarily. Harmless growths on the adrenal glands are common in the general population and can occur by coincidence in someone with cancer. A specific type of CT measurement, a washout study, an MRI or a PET scan usually distinguishes the two, and this matters a great deal, because assuming the wrong answer changes your whole treatment.
Why is it so important to be sure?
Because if it is a harmless growth, your cancer may still be treatable with the aim of cure. If it is wrongly assumed to be a spread, you could be moved to palliative treatment unnecessarily. The tests that distinguish them are straightforward and worth doing properly.
If it is a metastasis, is anything worth doing?
Often yes, particularly if it is the only site of spread and your original cancer is controlled. Removing a single adrenal deposit, or treating it with precisely targeted radiotherapy, gives long-term survival in a meaningful proportion of patients — especially with kidney cancer, melanoma and lung cancer. The longer the gap between the original cancer and this appearing, the better the outlook.
Surgery or radiotherapy?
Both achieve good local control. Keyhole surgery removes the gland in a one or two night stay. Stereotactic radiotherapy is delivered over a few outpatient visits with no operation at all and suits patients who are less fit or prefer to avoid surgery. The choice depends on the size and position of the deposit and on your general health.
Why do I need a blood or urine test before a biopsy?
Because one type of adrenal tumour produces adrenaline-like hormones, and putting a needle into it can cause a dangerous surge in blood pressure. It is a simple test, it takes little time, and it must be done first even when a metastasis is considered far more likely.
Can I manage with one adrenal gland?
Yes, entirely. A single healthy gland produces everything the body needs, and no replacement medication is required. Replacement is only necessary when both glands are extensively involved or both have been removed.
I feel exhausted and dizzy. Is that just the cancer?
It may be, but it should be checked. If both adrenal glands are affected, or if you are receiving immunotherapy, these symptoms can indicate that your body is not producing enough of the steroid hormones it needs — a condition that is dangerous if missed but very treatable with tablets. Low blood pressure, low sodium or persistent nausea alongside the tiredness makes it more likely, and it warrants a prompt blood test rather than being put down to the illness.
What is the emergency I should know about?
If you are on steroid replacement, becoming unwell — with a fever, vomiting, diarrhoea or an injury — means your body needs more steroid than usual, and failing to increase it can be life-threatening. You should be given clear written instructions, a card to carry, and an emergency injection with training in how to use it. If this has not been provided, ask for it.
Related conditions
Other conditions of the adrenal glands covered on this site:
This page provides general information and does not replace an individual medical consultation. Assessment and treatment are decided for each patient after review of their history, examination, investigations and discussion in a multidisciplinary meeting.
