

Conditions in this group
This group includes wandering spleen, torsion of a wandering spleen, accessory spleen, splenogonadal fusion, and splenosis.
How they develop and how they are diagnosed
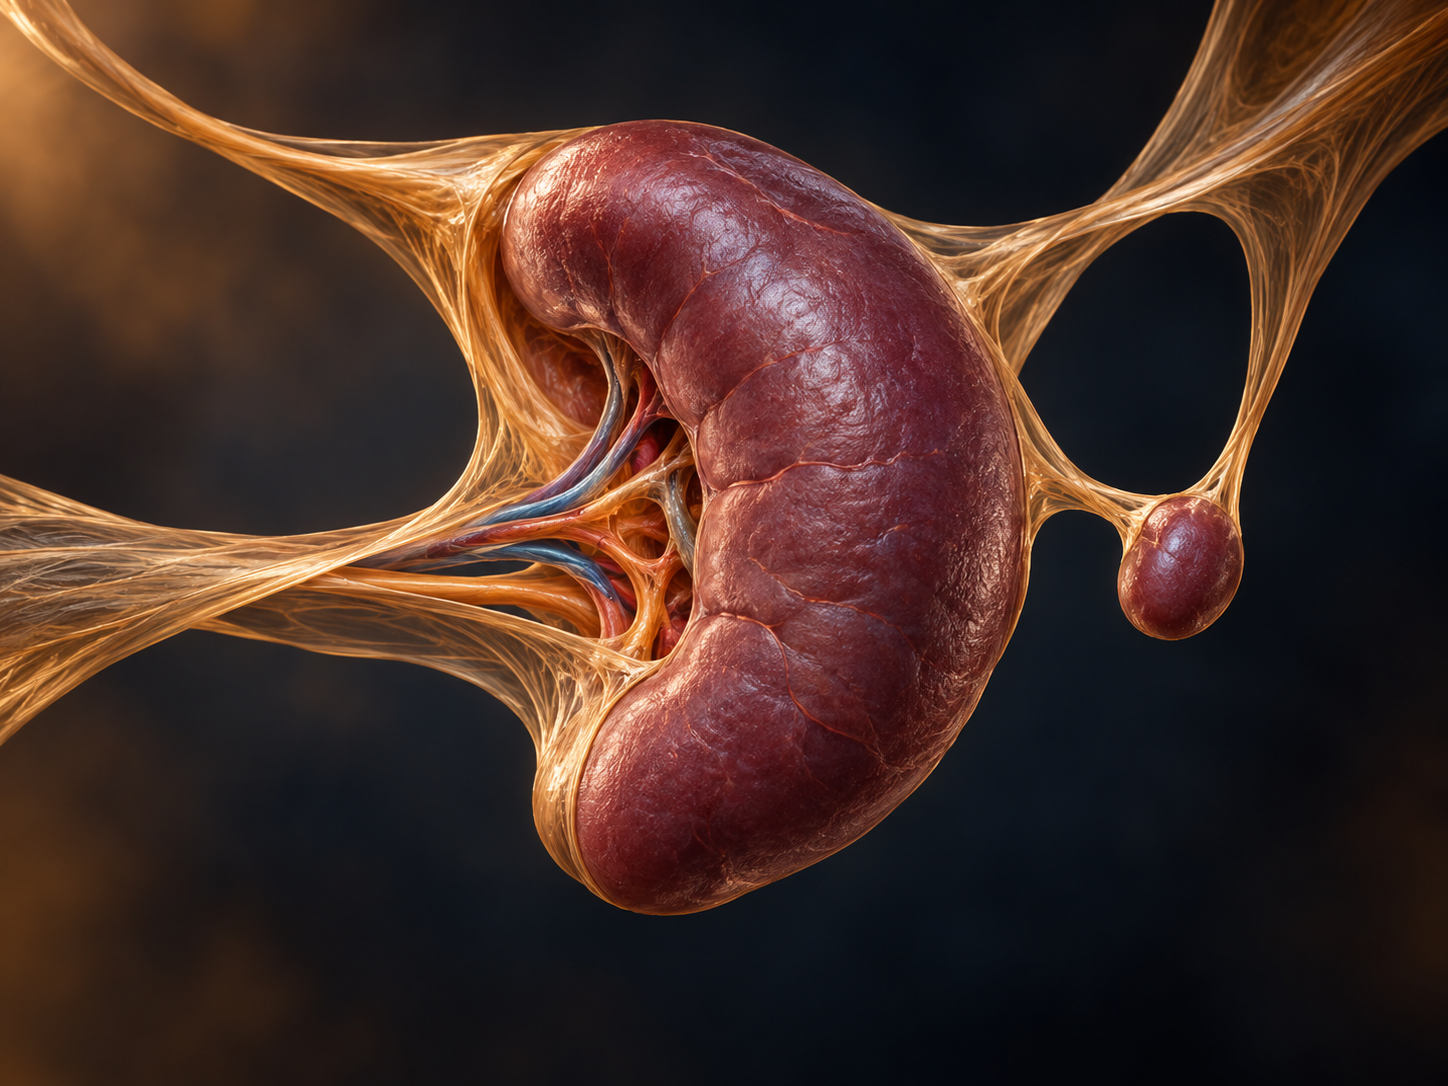
A wandering spleen results from laxity or absence of the ligaments that hold it in place. It may move within the abdomen or pelvis and twist around its vascular pedicle. Torsion can lead to acute pain and infarction. An accessory spleen is a small additional focus of splenic tissue and is particularly important when splenectomy is performed for a hematological condition. Splenosis is implantation of splenic tissue after trauma or previous splenectomy.
CT or MRI shows the position of the spleen, its blood supply, and the presence of accessory splenic tissue. In acute torsion, diagnosis is urgent.
Treatment
For a wandering but viable spleen, splenopexy, meaning surgical fixation of the organ, may be performed. When there is infarction or a nonviable spleen, splenectomy may be needed. An accessory spleen or splenosis usually needs no treatment unless it is associated with persistence of a hematological disease, symptoms, or diagnostic uncertainty.
Frequently asked questions
Is wandering spleen an emergency?
Acute pain may indicate torsion and requires immediate assessment.
Why is an accessory spleen sought before splenectomy?
In some hematological conditions, remaining functioning accessory tissue may limit the expected therapeutic effect.
Is splenosis cancer?
No. It is a benign implantation of splenic tissue, but can sometimes mimic other lesions on imaging.
When to seek medical attention
An accessory spleen or splenosis rarely causes symptoms. A wandering spleen is different: it can twist on its stalk and lose its blood supply. Seek emergency care for sudden, severe abdominal pain, especially with vomiting, or a tender lump in the abdomen that has suddenly appeared or changed position. Milder, on-and-off pain, a feeling of a mass that moves, or early fullness after eating should also be assessed.
What the assessment involves
Ultrasound with Doppler and contrast-enhanced CT show where the spleen lies, how it is attached, and whether blood is flowing normally. In a suspected twist, the scan is arranged urgently. Small accessory spleens and splenosis deposits are usually found by chance on scans done for another reason, and recognizing them avoids unnecessary biopsy or surgery, because they can look like tumors.
Treatment and recovery
A wandering spleen that is still healthy is usually fixed in place with a keyhole operation (splenopexy), which keeps the spleen. Recovery is usually quick, with a short hospital stay and a return to light activity within one to two weeks, while heavy lifting is avoided for about four to six weeks. If the spleen has lost its blood supply and cannot be saved, it is removed, and the vaccination and fever advice in the splenectomy article applies.
An accessory spleen or splenosis needs no treatment unless it causes symptoms, or unless a blood condition such as immune thrombocytopenia returns after a splenectomy, when removing the extra tissue may be discussed.
More questions about these conditions
Is an accessory spleen harmful?
No. It is a small extra piece of normal spleen tissue seen in a sizeable minority of people and is harmless in most.
Why does a spleen become a wandering spleen?
The ligaments that normally hold the spleen in place are absent or loose, from birth or because they stretch over time. It is more often recognized in children and in women of childbearing age.
Do I need treatment if I have no symptoms?
Not always. A wandering spleen carries a risk of twisting, so many surgeons recommend fixing it once it is found. Accessory spleen and splenosis are usually just observed.
